Call for Appointment : 0712 6692706
Call Support 07126692706

Midlife & Menopause · Nagpur

Menopause Treatment in Nagpur

Menopause is not an illness, and it is also not something you are required to endure in silence. Dr. Kunda Shahane assesses perimenopausal and menopausal symptoms, performs the pelvic ultrasound in the same consultation, prescribes and supervises hormone therapy where it is appropriate, and investigates any bleeding that occurs after the menopause herself. MBBS · MS (Obs & Gynae) · FIFM · FMF (London).

Hormone therapy prescribed here Scan in the same visit Bleeding after menopause investigated English · Hindi · Marathi
46.6Mean age at menopause in India, in years
75%Of postmenopausal Indian women report hot flushes and night sweats
12Months without a period before menopause is confirmed
90%Of endometrial cancers present with bleeding after menopause
Who you will see

A gynaecologist who scans, prescribes and operates

Menopause care in most of Nagpur is split across at least three people: someone who listens to the symptoms, someone else who performs the ultrasound, and a third person if a procedure turns out to be needed. Every handover is a place where the story is retold and something is lost.

Dr. Kunda Shahane qualified MBBS in 2004, completed MS in Obstetrics & Gynaecology at Government Medical College, Nagpur, and taught obstetrics and gynaecology as Assistant Professor for three years before subspecialising in ultrasound and fetal medicine. Gynaecology is the training that came first. In a menopause consultation that means one person takes the history, performs the pelvic ultrasound, decides whether the endometrium needs sampling, writes the hormone prescription if one is indicated, and reviews you afterwards.

It also means the scan is interpreted by the person who asked the question. An endometrial thickness of 6 mm means something quite different in a woman who is bleeding two years after her last period, a woman on hormone therapy, and a woman with no symptoms at all. That is an interpretation problem, not an imaging problem, and it is the reason the scan and the consultation belong in the same room.

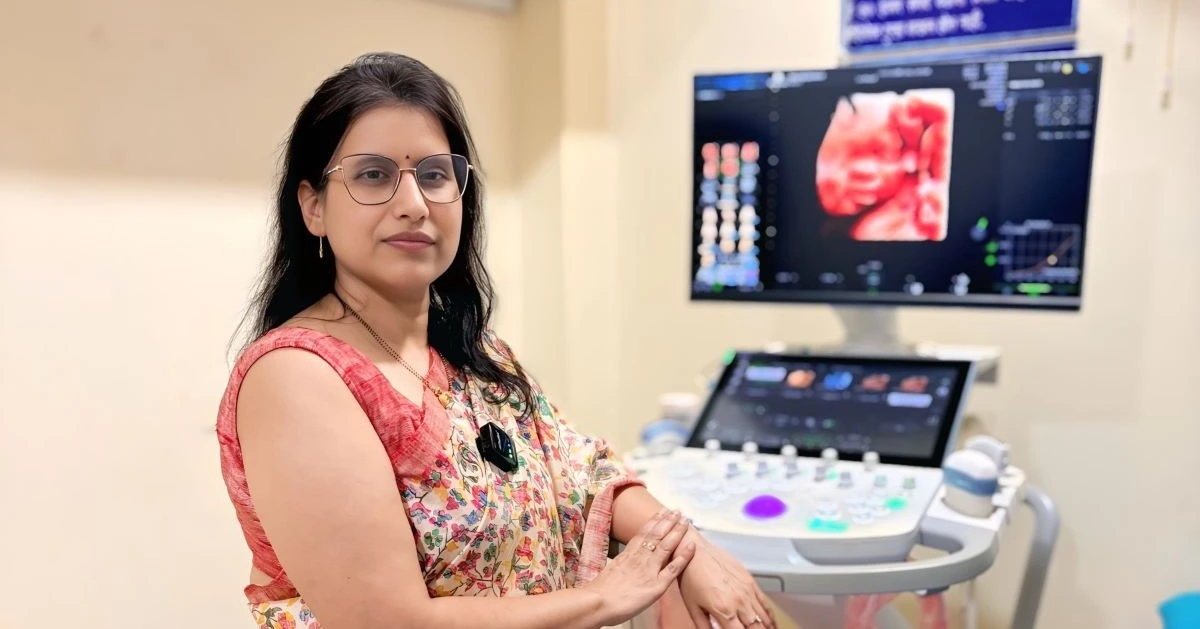
Dr. Kunda Shahane, gynaecologist and fetal medicine specialist — menopause consultation, Mayflower Fetal Medicine Centre Nagpur

The three stages

Perimenopause, menopause, and the years after

Perimenopause is the transition, and it is where most of the confusion lives. Cycles shorten, then lengthen, then skip. Bleeding can become heavier before it stops altogether. Hot flushes, disturbed sleep, irritability and difficulty concentrating begin while periods are still happening, which is precisely why they are so often attributed to stress, thyroid disease or "hormonal imbalance" instead. In India this phase commonly begins in the late thirties or early forties.

Menopause itself is a single point in time, identified backwards: twelve consecutive months with no period. In a woman over 45 with typical symptoms, that history is the diagnosis. Guidelines are explicit that hormone tests should not be used to identify perimenopause or menopause at this age, because FSH fluctuates from week to week and the result does not change management. Below 45 the tests become useful again, and below 40 they are essential, because that is a different diagnosis.

Postmenopause is everything afterwards. Hot flushes usually fade over a few years. Vaginal and urinary symptoms usually do not — they tend to progress — and the consequences of low oestrogen for bone accumulate quietly. Indian women reach menopause around four to five years earlier than the widely quoted global average of 51, which means more years spent in this phase, not fewer.

Two situations are not simply "early versions" of the same thing. Menopause between 40 and 45 is early menopause; periods stopping before 40 is premature ovarian insufficiency. Both are assessed differently, and in both, hormone treatment is usually continued at least to the average age of menopause for reasons of bone and cardiovascular health rather than symptom relief alone. Surgical menopause, after removal of both ovaries, is abrupt rather than gradual and the symptoms are correspondingly more severe.


Why women actually come

Five situations, and what is done about each

"I am 43 and my periods have gone haywire"

Cycles that have become irregular in the early forties are usually perimenopausal, but "usually" is not a diagnosis. Thyroid disease, anaemia, a fibroid, a polyp and pregnancy all produce the same complaint, and a scan in the same visit settles most of it. Where the bleeding itself is the problem rather than the cycle length, it is assessed as abnormal uterine bleeding and treated on its own terms — several of the treatments that help heavy perimenopausal bleeding also provide contraception, which is still needed at this age.

"The hot flushes and the sleeplessness are ruining my work"

This is the symptom cluster hormone therapy treats best, and the question that actually decides treatment is not how bad the flushes sound but what they are costing you — sleep, concentration, patience, the ability to sit through a meeting. Dr. Kunda asks that question directly. If treatment is appropriate she prescribes it and reviews you; if your history makes hormones unsuitable, she says so and offers what else is available rather than leaving you with nothing.

"I bled again, two years after my periods stopped"

This is the one symptom on this page that should not wait. Most causes are benign, but around nine in ten women diagnosed with endometrial cancer present exactly this way, and the point of the appointment is to establish which it is. The assessment is a transvaginal ultrasound and, in most cases, endometrial tissue sampling — see the section below on why that has changed. Related patterns of bleeding are covered on the vaginal bleeding page.

"Sex has become painful and I have kept quiet about it"

Genitourinary syndrome of menopause — dryness, burning, painful intercourse, urinary urgency, recurrent urinary infection — is the most under-reported part of menopause and one of the most treatable. It does not resolve on its own the way flushes eventually do. Examination is what separates it from an infection or a skin condition, and treatment is straightforward. Where leakage is the dominant symptom it is assessed as urinary incontinence, which is far more treatable than most women are told.

"My periods stopped at 36 and I was told to accept it"

Premature ovarian insufficiency is not early menopause and should not be managed as though it were. It warrants hormone tests, a search for a cause, a conversation about fertility that is honest in both directions, and in most cases hormone treatment continued until around the usual age of menopause — because at 36 the issue is decades of oestrogen deficiency, not a few difficult years. Where fertility is the concern, it is assessed on the infertility evaluation pathway.

What changed in 2026

Bleeding after the menopause: the scan is no longer enough by itself

For most of the last decade, the accepted first step for a first episode of postmenopausal bleeding was a transvaginal scan. If the endometrium measured 4 mm or less, that was taken as sufficient reassurance and sampling was reserved for women who kept bleeding or who had risk factors. That rule came from ACOG Committee Opinion 734, published in 2018.

In April 2026 ACOG revised it. The current recommendation is that transvaginal ultrasonography and endometrial tissue sampling are both part of the initial evaluation for most patients with postmenopausal bleeding. The reason is straightforward and uncomfortable: the thickness-based approach had lower sensitivity than assumed, performed particularly poorly for the aggressive subtypes of endometrial cancer, and performed worst in exactly the women least likely to be offered a second opinion.

This is worth explaining on a clinic page because a patient who read about the 4 mm rule — or a doctor who has not revisited it — may reasonably believe a normal scan closes the matter. It usually does not.

What this means in practice here. Dr. Kunda performs the transvaginal scan herself, and where sampling is indicated she performs the hysteroscopy and curettage herself, at the hospitals in Dhantoli where she is attached. The scan is not a gatekeeping step performed by someone who will never see you again. Sampling is a decision, made with you, and it is neither automatic nor refused on request — persistent or recurrent bleeding warrants histology whatever the measurement showed.

Hysteroscopy also answers the question the scan raises. Where a thickened endometrium turns out to be an endometrial polyp or a submucosal fibroid, seeing the cavity directly is what distinguishes it from a diffuse abnormality, and the polyp can be removed in the same sitting.

Treatment

What is actually available, and who each option suits

There is no single menopause treatment, and the decision is not "hormones or nothing". What follows is the honest shape of the options. Which of them applies to you is a consultation, not a web page.

Systemic hormone therapy

The most effective treatment for hot flushes and night sweats, and it also protects bone. Oestrogen is given by tablet, patch or gel; if you still have a uterus, a progestogen is added to protect the endometrium — this is not optional. For most healthy women under 60, or within ten years of the menopause, and with no contraindication, the balance of benefit and risk favours treatment. Starting for the first time well outside that window requires a higher threshold and a more careful conversation.

Vaginal oestrogen

A low dose applied locally, for dryness, painful intercourse and the urinary symptoms that accompany them. Very little is absorbed into the bloodstream, which is why it can be used at any age, for extended periods, and by many women for whom systemic hormones are not appropriate. It treats genitourinary symptoms only — it will not help hot flushes — and the benefit stops when the treatment stops.

Non-hormonal options

For women who cannot take hormones or do not wish to, several non-hormonal prescription treatments reduce vasomotor symptoms, and cognitive behavioural approaches have evidence for flushes and for sleep. Vaginal moisturisers and lubricants are useful in their own right. These are genuinely less effective than hormone therapy for flushes, and saying otherwise would be dishonest — but "less effective" is not "no use".

What treatment can reasonably do

  • Substantially reduce hot flushes and night sweats
  • Improve sleep that is broken by night sweats
  • Relieve vaginal dryness and painful intercourse
  • Reduce urinary urgency and recurrent urinary infections related to low oestrogen
  • Slow bone loss while it is being taken
  • Be reviewed, adjusted and stopped — nothing here is a life sentence

What it cannot do, and what is not offered

  • Reverse the menopause or restore fertility
  • Guarantee protection from heart disease, dementia or cancer
  • Substitute for investigating bleeding after the menopause
  • Continue protecting bone once it is stopped
  • Bone density scanning and osteoporosis treatment — not done here
  • Energy-based vaginal devices — not established treatment, not offered
Said plainly

Bone health is raised here, but not treated here

Bone loss accelerates in the years around the menopause, and an earlier menopause means the clock starts sooner. That is a genuine reason to think about bone in your forties rather than your sixties, particularly if you had a premature or surgical menopause, a low body weight, a long gap on steroids, or a parent who fractured a hip.

What happens at this clinic is that the subject is raised, your risk is discussed, weight-bearing activity and adequate calcium and vitamin D are covered, and bone protection is factored into the hormone therapy decision. What does not happen here is bone density scanning, and Dr. Kunda does not manage osteoporosis treatment. She will tell you when a bone density test is worth having and direct you to a physician for it. A clinic page that implied otherwise would be inviting you to travel for something you would not receive.

Your appointment

What a menopause consultation involves

  1. The history, in your own wordsBring the date of your last period if you know it, a list of the medicines you take, any previous scan or blood reports, and — if you can — a rough note of how the symptoms are affecting your sleep and your day. That last item changes the treatment decision more than any measurement does.
  2. ExaminationAn abdominal and, where appropriate, an internal examination. This is how genitourinary syndrome of menopause is distinguished from an infection or a skin condition, and it is explained before it is done. You may ask for it to stop at any point.
  3. Ultrasound in the same roomTransabdominal, transvaginal, or both. You will be told what is being seen as it is being seen, rather than waiting for a report to be typed and taken to another doctor.
  4. Tests, only where they change somethingThyroid function, haemoglobin and, in women under 45, hormone levels — ordered when the picture does not fit rather than as routine. Cervical screening is offered if your Pap smear is due, since this is a common age to have fallen behind on it.
  5. The plan, with the trade-offs statedWhat is causing the symptoms, what the options are including doing nothing, and what each one can and cannot deliver. If hormone therapy is appropriate, the prescription is written here, with the review date set at the same time.
  6. A procedure, if one is indicatedWhere the endometrium needs sampling, hysteroscopy and curettage are arranged at hospital and performed by Dr. Kunda. The histopathology report is explained to you by the same person who took the sample.

Who holds the thread afterwards

Menopause is not an appointment, it is a decade. Symptoms change, hormone therapy needs reviewing, a smear falls due, bleeding appears years after it should have stopped. The value of being seen by a gynaecologist who does her own scanning and her own surgery is not just the single visit — it is that the same person holds the history when something changes three years later, and there is no fresh handover to explain everything again.

All women’s health services · About Dr. Kunda Shahane · Contraception in perimenopause · Abnormal vaginal bleeding

What it costs

The consultation, the ultrasound and any procedure are charged separately, and what you need is decided at the visit rather than sold in advance. Hormone therapy is a prescription you fill at a pharmacy, and prices differ substantially between preparations — a patch and a tablet are not the same cost, and neither is a three-month supply against a one-month one.

ItemHow it is charged
Menopause consultationCharged as a gynaecology consultation; current rate given before the visit
Pelvic ultrasoundCharged separately, and only when indicated
Hysteroscopy and curettageHospital procedure — quoted separately, including anaesthesia and histopathology
Hormone therapyA pharmacy cost, not a clinic cost; varies by preparation

WhatsApp +91 8087471244 with what you have been advised to have and you will be given the current charge before anything is done. No payment is taken to book.

Questions patients ask

Menopause — frequently asked questions

How do I know if I am in menopause or if something else is wrong?

Menopause is confirmed in hindsight: twelve consecutive months with no period, once pregnancy and other causes are excluded. Before that point you are in perimenopause, when cycles shorten, lengthen or skip while hot flushes and sleep disturbance begin. For a woman over 45 with these symptoms, guidelines advise diagnosing perimenopause and menopause on history alone, without hormone tests, because FSH swings from week to week and knowing the number does not change what is done. Tests are used differently below 45, and thyroid disease, anaemia and pregnancy are still checked when the picture does not fit.

At what age does menopause usually happen in India?

Earlier than the figure most international websites quote. A systematic review of Indian studies put the mean age at menopause at about 46.6 years, roughly four to five years earlier than the frequently cited global average of 51. That matters beyond curiosity: an earlier menopause means more years of life after oestrogen falls, which is the reason bone and heart health are raised at the first consultation rather than a decade later.

I have started bleeding again two years after my periods stopped. Is that serious?

It needs to be investigated, promptly, and never watched. Around 90% of women diagnosed with endometrial cancer present with bleeding after the menopause. Most causes turn out to be benign — a thin, atrophic lining, a polyp, a fibroid, an infection or the effect of a medicine — but the purpose of the appointment is to establish which of those it is rather than to reassure you on probability. Come in rather than waiting to see whether it happens again.

Is an ultrasound enough to check bleeding after menopause?

Not on its own, in most cases. Until recently a transvaginal scan showing an endometrium of 4 mm or less was accepted as sufficient for a first episode of postmenopausal bleeding. In April 2026 ACOG revised that position and now recommends both transvaginal ultrasonography and endometrial tissue sampling as part of the initial evaluation for most patients, because the thickness rule missed too many cancers, particularly the aggressive subtypes and particularly in some groups of women. Dr. Kunda performs the scan and, where sampling is indicated, the hysteroscopy and curettage herself.

Where is the hysteroscopy and D&C done, and will I be admitted?

Consultation, examination and ultrasound are done at Mayflower Clinic, Dhantoli. Hysteroscopy and curettage are performed by Dr. Kunda at the hospitals in Dhantoli where she is attached, because they need anaesthesia and a theatre. It is usually a day procedure. What is involved, what the anaesthetic entails and when the histopathology report is expected are explained before you consent, not afterwards.

Do you prescribe hormone therapy, or will I be sent to someone else?

Dr. Kunda prescribes and supervises menopausal hormone therapy herself, both systemic treatment for hot flushes and night sweats and local vaginal oestrogen for dryness and urinary symptoms. The assessment before starting, the choice of preparation and route, the progestogen needed to protect the lining if you still have a uterus, and the review afterwards are all part of the same consultation rather than a referral elsewhere.

Is hormone therapy safe? I have read frightening things about it.

The honest answer is that it depends on your age, how long ago your periods stopped and your own medical history, which is why the decision is made in a consultation rather than from a website. For most healthy women under 60, or within ten years of the menopause, and without contraindications, the balance of benefit and risk favours treatment for troublesome hot flushes and for protecting bone. Starting for the first time well beyond that window shifts the balance and needs a higher threshold. Hormone therapy is not suitable for everyone: a history of breast cancer, of a blood clot, of stroke or of unexplained vaginal bleeding changes the answer, and those are things she asks about first.

Has the safety advice on hormone therapy changed recently?

Yes, in one specific regulatory sense. In November 2025 the United States Food and Drug Administration began removing the boxed warning about cardiovascular disease, breast cancer and probable dementia from menopausal hormone therapy products, and approved revised labels for the first products in 2026; the boxed warning about endometrial cancer for systemic oestrogen-alone products was kept. That is a United States labelling decision. It does not by itself change what is written on an Indian product, which is approved separately, and it does not change the fact that the decision is individual. It is included here because patients read about it and deserve an accurate account of what did and did not change.

Vaginal dryness and pain during sex have become a problem. What can be done?

This is genitourinary syndrome of menopause, and it is common, treatable and persistently under-reported. Unlike hot flushes, it does not settle by itself with time; it tends to progress. Vaginal moisturisers and lubricants help, and low-dose vaginal oestrogen is effective and can be used at any age and for a long period, including by many women who cannot take systemic hormones. Energy-based vaginal devices marketed for these symptoms are not established treatment and are not offered here.

Do I still need contraception during perimenopause?

Yes. Ovulation becomes unpredictable rather than absent, and pregnancy is still possible while you are having occasional periods. The usual advice is to continue contraception for two years after the last period if you are under 50, and for one year after the last period if you are over 50. Which method suits you is worth discussing, because some also help with heavy perimenopausal bleeding.

Do you do bone density testing?

No. Bone density scanning is not done at this clinic and Dr. Kunda does not manage osteoporosis treatment. What she does is raise it: an earlier menopause means a longer period of low oestrogen, so she will tell you when a bone density test is worth having and who to see for it, and will factor bone protection into the hormone therapy discussion. Saying this plainly is better than implying a service that is not provided here.

My periods stopped in my thirties. Is that the same thing?

No, and it should not be treated as an early version of the same event. Periods stopping before 40 is premature ovarian insufficiency, and it needs a different assessment — including hormone tests, which are genuinely useful at that age — and, in most cases, hormone treatment continued at least until the usual age of menopause, for bone and cardiovascular protection rather than for symptom relief alone. It also has implications for fertility that deserve a proper conversation rather than a leaflet.

What will the consultation cost?

The consultation, the ultrasound and any procedure are charged separately, and what you actually need is decided at the visit rather than booked in advance. WhatsApp +91 8087471244 with what you have been advised to have and you will be given the current charge before anything is done. No payment is taken to book.

Will I be seen by a female doctor, and how soon?

Yes — Dr. Kunda Shahane conducts the consultation, the examination and the ultrasound herself. The clinic is open Monday to Saturday, 10:00 AM to 6:00 PM, and closed on Sunday. Appointments are usually available within a few days; if you are bleeding after the menopause, say so when you book and you will be given an earlier slot.

In Dr. Kunda’s words
When a woman tells me she’s been advised to ‘just manage’ menopause symptoms like hot flushes or poor sleep, I ask how it affects her daily life. Menopause isn’t an illness, but symptoms shouldn’t be ignored. We discuss lifestyle, bone health, and hormone therapy to tailor a decision based entirely on her priorities.
Dr. Kunda Shahane MBBS · MS (Obs & Gynae) · FIFM · FMF (London)

Sources for the figures and guidance on this page

  1. Prasad JB, Tyagi NK, Verma P. Age at menopause in India: a systematic review. Diabetes & Metabolic Syndrome, 2021 — mean age at menopause 46.6 years across 202 studies. View source
  2. Knowledge, attitudes and practices of young obstetricians and gynaecologists in menopause management in India, Cureus, 2025 — Indian Menopause Society context and the finding that 75% of postmenopausal Indian women report vasomotor symptoms. View source
  3. American College of Obstetricians & Gynecologists. Updated guidance on the role of transvaginal ultrasonography in evaluating the endometrium of individuals with postmenopausal bleeding. Clinical Practice Update, Obstetrics & Gynecology, April 2026 — transvaginal ultrasonography and endometrial tissue sampling at initial evaluation for most patients. View source
  4. ACOG Committee Opinion No. 734, Obstet Gynecol 2018;131:e124–9 — the earlier 4 mm endometrial thickness threshold, now superseded for initial evaluation. View source
  5. The Menopause Society. 2022 Hormone Therapy Position Statement, Menopause 2022;29(7):767–794 — favourable benefit-risk profile under 60 or within ten years of menopause; vaginal oestrogen usable at any age. View source
  6. NICE guideline NG23, Menopause: identification and management (2015, updated 2024) — diagnosis without laboratory tests at 45 and over; FSH reserved for ages 40–45 and for suspected premature ovarian insufficiency. View source
  7. U.S. Food and Drug Administration, 10 November 2025 — initiation of boxed-warning removal on menopausal hormone therapy products, with the endometrial cancer warning retained for systemic oestrogen-alone products. View source
  8. U.S. Food and Drug Administration, 2026 — approval of revised labelling for the first six menopausal hormone therapy products. View source

Written and medically reviewed by Dr. Kunda Shahane, MBBS, MS (Obs & Gynae), FIFM, FMF (London) · Last reviewed: 1 September 2026

Related

Other women’s health services in Nagpur

Book a menopause consultation

Tell us what the symptoms are costing you — sleep, work, comfort — and Dr. Kunda will tell you honestly what can and cannot be improved. If you are bleeding after the menopause, say so when you book and you will be seen sooner. Mayflower Clinic, Surdham Complex, Behind Silver Palace Building, 2nd Lane from Panchsheel Square, Opp. Yashwant Stadium, Dhantoli, Nagpur – 440012.

Monday–Saturday, 10:00 AM – 6:00 PM · Sunday closed · contact@mayflowerclinic.in

PCPNDT Act Notice: Mayflower Fetal Medicine Centre strictly complies with the Pre-Conception and Pre-Natal Diagnostic Techniques (Prohibition of Sex Selection) Act, 1994. Sex determination and sex-selective practices are strictly prohibited and punishable by law. All ultrasound and prenatal diagnostic services at this centre are performed exclusively for lawful medical indications — fetal anatomy assessment, fetal wellbeing, and diagnosis of maternal-fetal conditions. Disclosure of fetal sex is illegal and is not performed at this centre under any circumstances. Read our full PCPNDT compliance statement.
Medical Disclaimer: This page is for general patient education only and does not constitute medical advice, diagnosis, or treatment. Please consult Dr. Kunda Shahane or your treating gynaecologist for advice specific to your situation.